Haemorrhoids, commonly called piles, are one of the most common conditions in surgical practice. Almost every doctor sees this condition often. This chapter explains piles in full. It covers presentation, examination, differential diagnosis, investigations, and management. This is the same pattern used for every disease chapter in this manual.
10.1 What Are Piles
Piles are not a new growth. They are enlarged, displaced anal cushions. Chapter 1 explained these cushions in detail. In a healthy person, the anal cushions help the anal canal close fully. They give a fine, watertight seal. Over time, these cushions can become swollen and congested. They may also slip downward, away from their normal position. This is what we call piles.
Piles can be internal or external. This depends on their position relative to the dentate line. Internal piles arise above the dentate line. They are usually painless, since this area has no pain-sensing nerves. External piles arise below the dentate line. They are usually painful, since this area is rich in pain-sensing nerves.
Piles affect people of all ages. They become more common with increasing age. Several factors increase the risk of developing piles. These include chronic constipation, and the straining that comes with it. Prolonged sitting on the toilet also raises the risk. So does a low-fibre diet. So does low fluid intake. Pregnancy is another common risk factor. This is due to raised pressure in the pelvis, and to hormonal changes. A family history of piles also plays a role. So does a sedentary lifestyle.
10.2 Classification of Internal Piles
Internal piles are graded by how far they prolapse, or come down, from the anal canal. This grading guides treatment choice.
First degree — the piles bleed, but do not prolapse. They stay inside the anal canal at all times.
Second degree — the piles prolapse on straining, but go back inside on their own.
Third degree — the piles prolapse on straining, and need to be pushed back manually.
Fourth degree — the piles stay prolapsed at all times, and cannot be pushed back.
This grading is simple, but very useful. It guides the doctor toward conservative treatment, office procedures, or surgery. These are explained later in this chapter.
Internal and external piles can also occur together. This is called a mixed, or combined, pile. A mixed pile has an internal component above the dentate line. It also has an external component below it. Treatment must address both parts. The chosen approach depends on which component is causing the main symptoms.
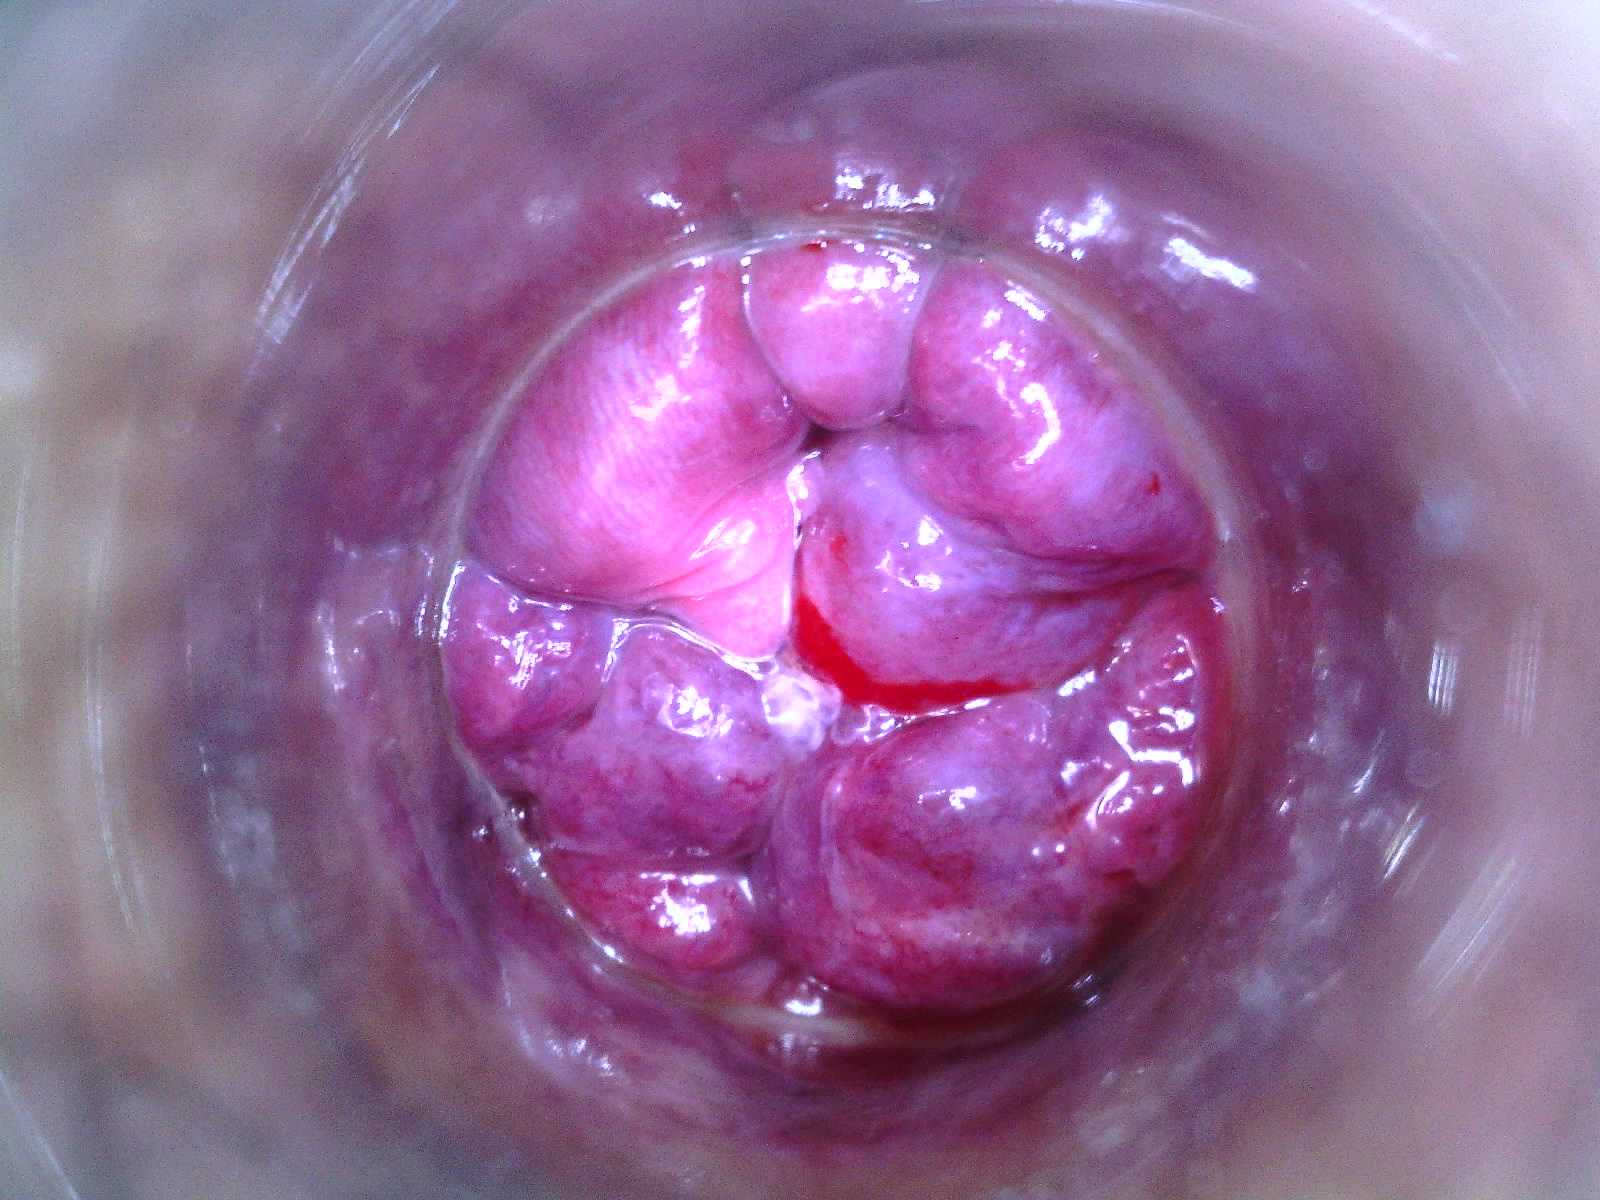
Fig. 10.A — Second-degree internal haemorrhoids, prolapsing on straining and reducing spontaneously.
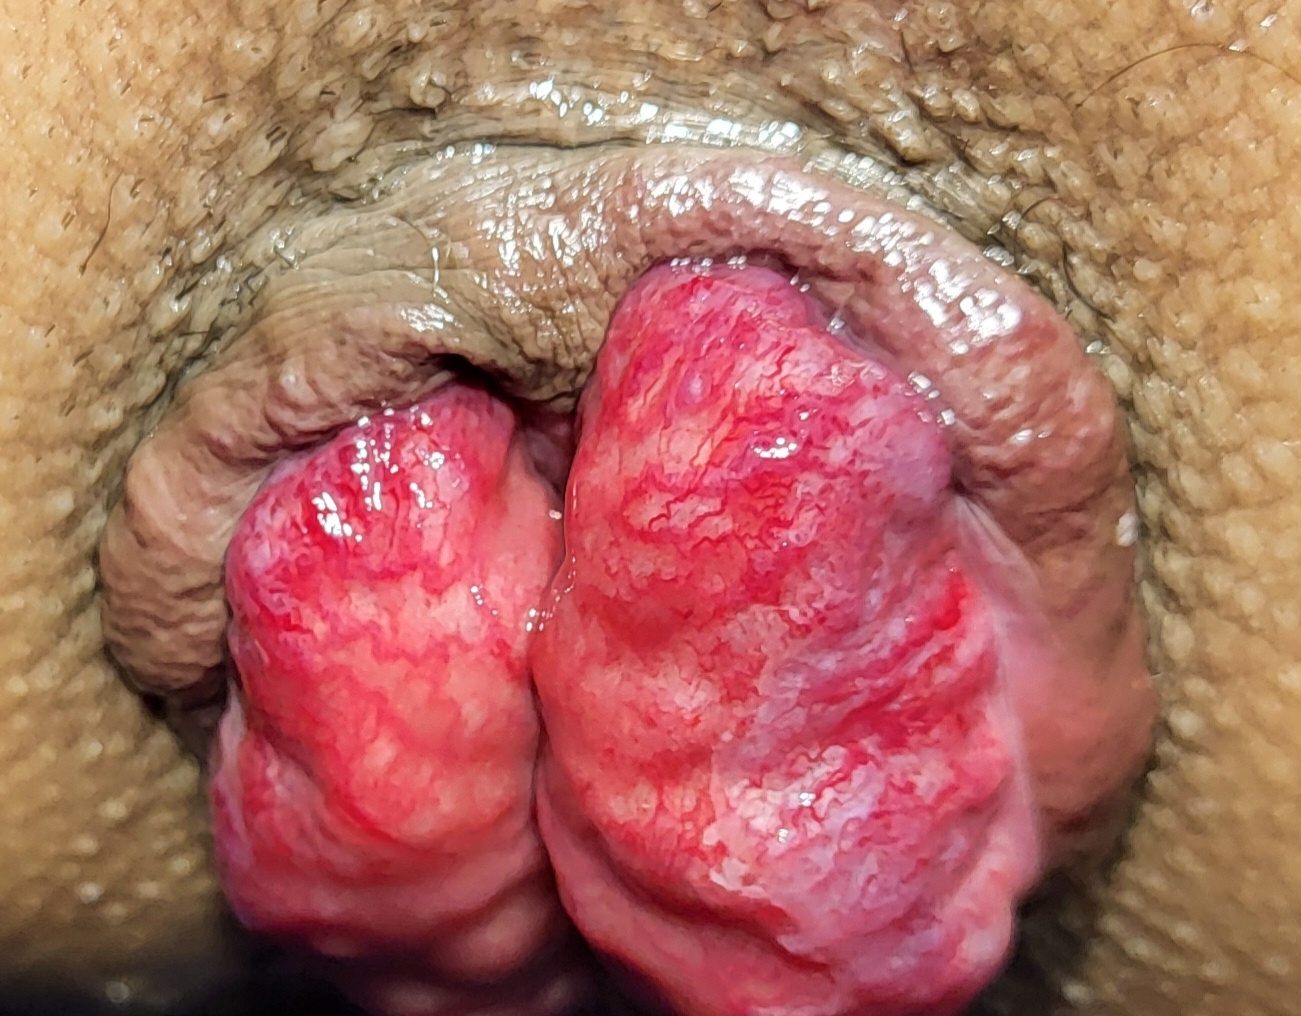
Fig. 10.B — Third-degree internal haemorrhoids, prolapsed on straining and requiring manual reduction.
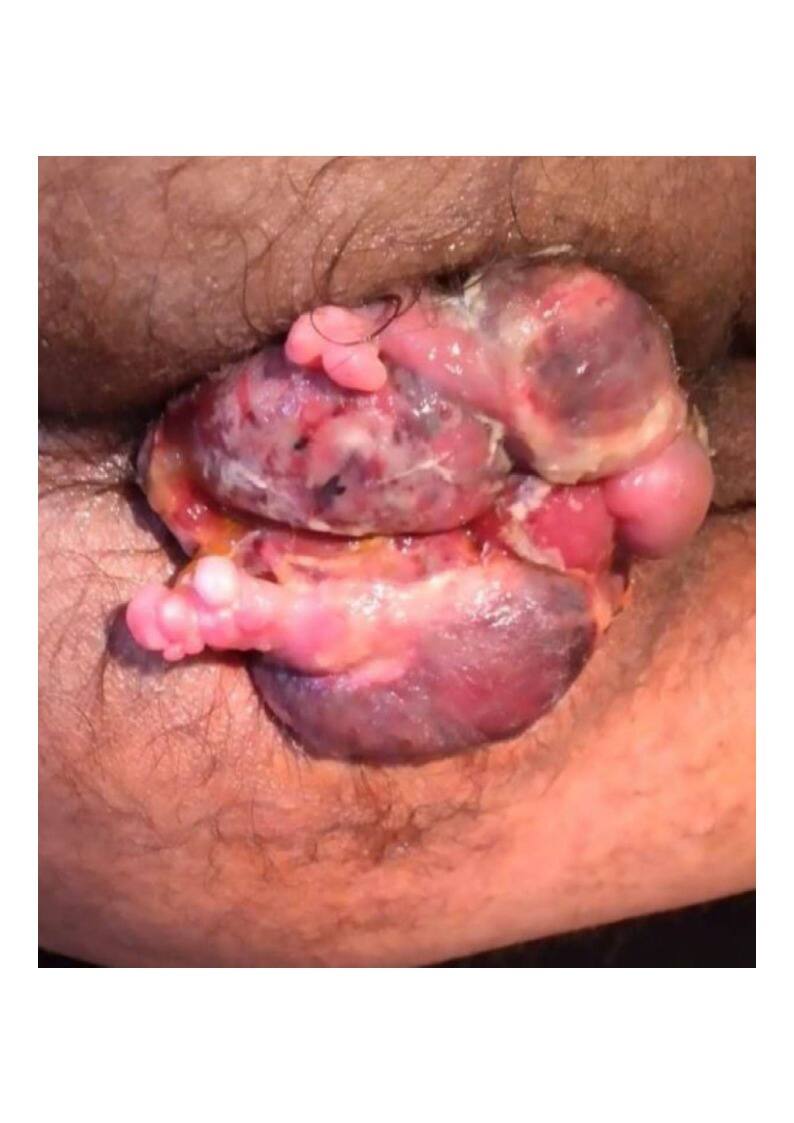
Fig. 10.C — Fourth-degree internal haemorrhoids, permanently prolapsed and irreducible.
10.3 Presentation
The history-taking approach for piles follows the method described in Chapter 2. Ask about each symptom in turn.
Bleeding — usually bright red, seen on the toilet paper or dripping after passing stool. The bleeding is usually painless.
Prolapse — a lump that comes down, especially with straining. Ask whether it goes back on its own, needs to be pushed back, or stays out permanently.
Discomfort — a dragging sensation, or mild discomfort, rather than sharp pain. Sharp pain suggests a complication, or a different diagnosis, such as a fissure.
Mucus discharge — common with larger, prolapsing piles. This can lead to irritation and itching around the anus.
Itching — from mucus discharge, or from difficulty keeping the area clean when piles prolapse.
Always ask the red flag questions from Chapter 2. These include age, weight loss, and any change in bowel habit. Bleeding must never be assumed to be from piles alone. A full assessment is always needed.
Ask also about the effect on daily life. Prolapsing piles can make sitting, walking, or working uncomfortable. Frequent soiling can affect a patient's confidence. It can affect their social life too. Understanding this impact helps the doctor judge how urgently treatment is needed, beyond the grade of the piles alone.
10.4 Examination
Follow the full sequence described in Chapter 3: inspection, palpation, digital rectal examination, and proctoscopy.
See Chapter 4 for the inspection method. Inspection may show external piles directly. It may also show internal piles that prolapse on straining.
See Chapter 5 for the digital rectal examination method. It is usually normal in simple piles, since soft piles are not easily felt. It remains essential, to rule out a mass or other abnormality.
See Chapter 6 for the proctoscopy method. Proctoscopy gives the clearest view. It shows the size, number, and position of the piles on the clock face. It also shows whether they prolapse into view on straining.
A thorough examination, following this sequence every time, prevents a common error. This error is diagnosing piles too quickly, without excluding other causes of bleeding.
Do not forget the general examination described in Chapter 3. Check for pallor. This can point to anaemia from long-standing bleeding. In a patient with heavy or prolonged bleeding, this general check is just as important as the local examination.
10.5 Differential Diagnosis
Several conditions can mimic piles, or occur alongside them. Always consider these possibilities.
Fissure-in-ano — causes sharp pain, usually with bleeding, and a visible tear on inspection.
Rectal prolapse — a full-thickness or mucosal prolapse. It is seen as circular or radial folds, rather than the grape-like clusters typical of piles.
Perianal abscess or fistula — causes swelling with pain, fever, or discharge. This differs from the typical painless bleeding of piles.
Anal or rectal growth — must always be considered. This is especially true with a change in bowel habit, weight loss, or bleeding mixed with the stool.
Skin tags — soft, painless folds of skin at the anal margin. They lack the bluish, vascular appearance of piles.
A patient can have piles and another condition together. Finding piles on examination does not exclude a more serious cause. This is especially true in an older patient, or one with red flag symptoms.
Consider a patient aged 55, with six weeks of bleeding and looser stools. Proctoscopy shows small, first degree piles. These piles alone do not explain a change in bowel habit. This patient needs colonoscopy, even though piles are visible. The change in bowel habit is a red flag that piles cannot fully explain.
10.6 Investigations
Most cases of piles are diagnosed on history and examination alone. This follows the approach in Chapter 8. Investigation is needed in specific situations.
Colonoscopy is needed in any patient with red flag symptoms. It is also needed in patients over 50 years old with new bleeding, even when piles are also found.
Blood tests, such as a full blood count, are useful if bleeding has been heavy or long-standing. This checks for anaemia.
Biopsy is taken if any lesion looks atypical, or does not fit the usual appearance of piles.
Investigation should never be skipped simply because piles have already been seen on examination. This is one of the most important lessons in anorectal practice.
Anorectal manometry and endoanal ultrasound are described in Chapter 8. They are not routinely needed for piles. They become useful only if there is coexisting concern about sphincter function, such as before considering surgery in a patient with borderline continence.
10.7 Conservative Management
Conservative treatment is the right first step for most first and second degree piles. It is also right for many third degree piles.
Increase dietary fibre, through fruits, vegetables, and whole grains. This softens the stool.
Increase fluid intake, to support the effect of fibre.
Avoid straining during defecation. Avoid spending long periods sitting on the toilet.
Use a stool softener, if dietary measures are not enough on their own.
Warm sitz baths ease discomfort and swelling. Take them for ten to fifteen minutes, several times a day.
Topical creams or suppositories can ease symptoms for a short period. They do not cure the underlying piles.
Give conservative treatment a fair trial, usually a few weeks. Plan a clear follow-up visit. If it fails, move to the next level of treatment without delay.
Patient education matters greatly here. Explain that piles are a mechanical problem, caused by pressure and straining. They are not an infection, and will not simply go away with medicine alone. A patient who understands this is far more likely to follow the dietary and lifestyle advice given.
10.8 Office and Outpatient Procedures
Several simple procedures can be done in the outpatient clinic. These suit mainly first, second, and some third degree piles.
Rubber band ligation — a small band is placed at the base of the pile. This cuts off its blood supply. The pile then shrinks and falls away within a few days. This is the most commonly used office procedure.
Sclerotherapy — a chemical solution is injected into the pile. This causes it to shrink over time. It is useful mainly for first and early second degree piles.
Infrared coagulation — heat energy is applied to the base of the pile. This causes it to shrink. It suits small, early piles well.
These procedures are quick. They need no anaesthesia in most cases. They allow the patient to return to normal activity the same day. They are not suitable for large, prolapsing piles, which usually need surgery.
After rubber band ligation, warn the patient about a dragging discomfort for a day or two. Warn them also that the pile will fall away within a week or so, sometimes with a small amount of bleeding. Serious bleeding, fever, or difficulty passing urine after the procedure should prompt an urgent review.
10.9 Surgical Management
Surgery is the right choice for third and fourth degree piles. It is also right for piles that have failed conservative and office treatment.
Open haemorrhoidectomy — the traditional operation. The pile mass is surgically removed. The wound is left open to heal. It remains highly effective, though recovery takes some weeks.
Closed haemorrhoidectomy — similar to the open technique. The wound is stitched closed at the end of the operation.
Stapled haemorrhoidopexy — a circular stapling device lifts the prolapsing tissue back into place. It also interrupts its blood supply. Recovery is often quicker than with traditional haemorrhoidectomy. The risk of recurrence is somewhat higher.
LigaSure or similar energy-device haemorrhoidectomy — uses a sealing device to remove the pile. This causes less bleeding, and often less pain, than the traditional open technique.
Doppler-guided haemorrhoidal artery ligation — locates and ties off the arteries feeding the piles, without removing tissue. This suits patients wanting a less invasive surgical option.
The choice between these techniques depends on the grade of piles, the equipment available, and the surgeon's experience. Explain the options clearly to the patient, following the approach described in Chapter 9. Do this before taking consent.
After any haemorrhoidectomy, good pain control is essential. Warm sitz baths, stool softeners, and adequate fibre and fluid intake all help the patient recover comfortably. Advise the patient to avoid straining. Advise them to attend the planned follow-up visit, so healing can be checked.
10.10 The OPB-BIG Technique for Giant Haemorrhoids
A small number of patients present with giant haemorrhoids. These are far larger than the usual fourth degree pile. A giant haemorrhoidal mass can reach 10 to 12 centimetres or more. This can approach the width of the patient's own thigh. Standard haemorrhoidectomy technique needs an important modification in these cases, to stay safe.
The author has developed a technique for these giant cases. It is named the OPB-BIG technique. This stands for Bhandari's Index-Guided vessel-sealer haemorrhoidectomy. The name reflects both its origin, and the giant size of the piles it was designed to treat.
The technique works as follows:
A vessel-sealing energy device, such as LigaSure, is used to divide and seal the tissue of the giant pile mass. This follows the same principle as standard energy-device haemorrhoidectomy.
The surgeon's gloved index finger is placed inside the anal canal throughout the dissection. This finger acts as a guide and a protective barrier.
The finger lets the surgeon feel the plane of dissection directly. It helps keep the vessel sealer working at a safe distance from the sphincter muscle and the anal canal wall.
This digital guidance is especially valuable in giant piles. Here, the distorted anatomy makes the usual visual landmarks harder to judge.
This technique aims to combine two benefits. It gives the reduced bleeding and reduced pain already seen with vessel-sealer haemorrhoidectomy. It adds a real-time, tactile safeguard against injury to the sphincter and canal wall, guided by the surgeon's own finger.
The patient was a man in his early fifties, with an irreducible prolapse of five years’ duration and a fifteen-year history of intermittent bleeding. The mass was not a single dominant pile but a massive circumferential swelling, gangrenous in areas, measuring approximately 12 cm — comparable in size to the patient’s own thigh.
At six-week follow-up, the patient had achieved complete wound healing with full continence — no incontinence of flatus or stool, no urgency, and a normal defecation pattern, with no complications recorded.
Fig. 10.1 — Pre-operative appearance: giant circumferential haemorrhoidal mass, approximately 12 cm, with gangrenous change.
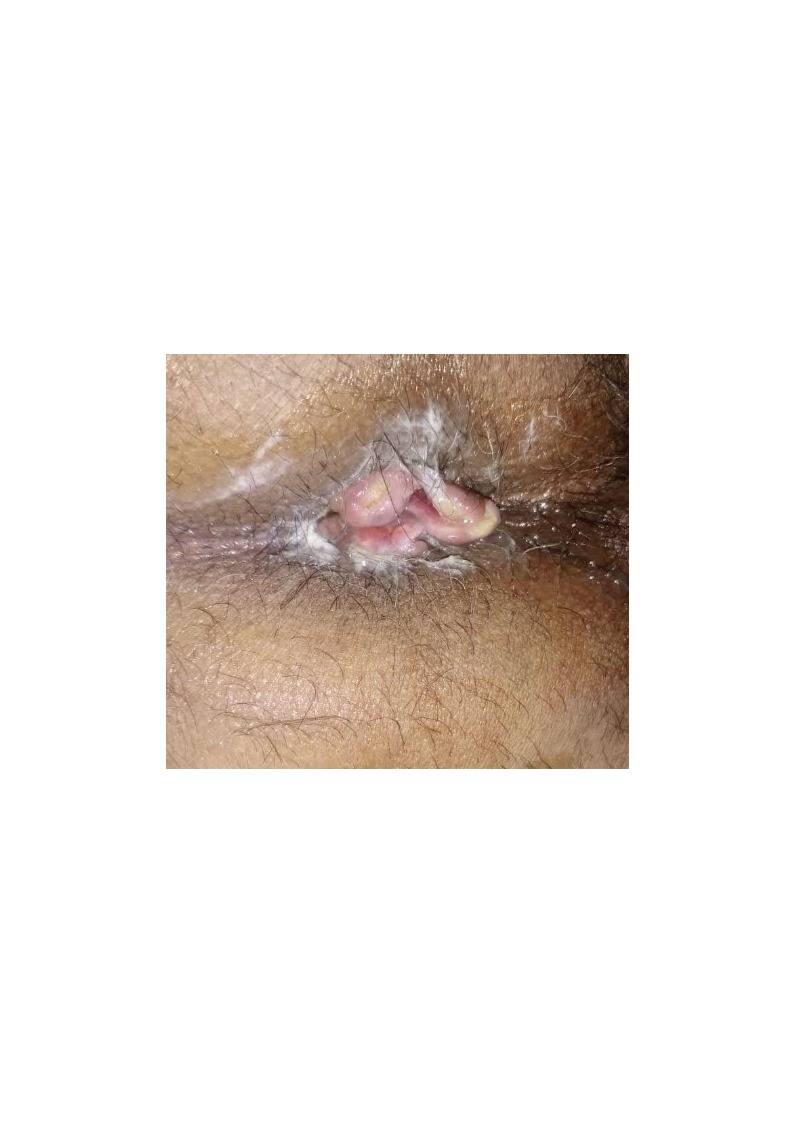
Fig. 10.2 — Post-operative appearance at six weeks: healed wound, normal perianal topography, full sphincter control confirmed.
This technique, and the case series behind it, is intended for a dedicated report in the GSP-SPCI journal, alongside its description here.
10.11 Special Situations
A few situations need special care.
Thrombosed external pile — a sudden, very painful, bluish swelling at the anal margin, caused by a blood clot. Seen early, within 48 to 72 hours, it can be treated by surgical removal of the clot for fast relief. Seen later, conservative treatment alone is usually preferred, since the clot is already resolving.
Strangulated prolapsed piles — a fourth degree pile that becomes trapped outside the anus, with its blood supply cut off. This is a surgical emergency. It needs urgent attention.
Piles in pregnancy — very common, especially in the third trimester. Conservative treatment is preferred wherever possible. Surgery is reserved for severe symptoms that do not respond to simple measures. It is usually deferred until after delivery, if it can safely wait.
Piles with anaemia — significant, long-standing blood loss needs correction of the anaemia, alongside treatment of the piles themselves.
10.12 Complications of Treatment
Every treatment, conservative or surgical, carries some risk. Explain these clearly to the patient beforehand.
Bleeding, in the days following any procedure or surgery.
Pain, which is usually most severe in the first week after open or closed haemorrhoidectomy.
Difficulty passing urine, in the first day or two after surgery, due to pain and local swelling.
Anal stenosis, a narrowing of the anal canal, if too much tissue is removed, or if healing is poor.
Recurrence of piles, particularly after office procedures, or after stapled haemorrhoidopexy.
A patient who understands these risks in advance copes far better if any of them occur.
10.13 Preventing Recurrence
Piles can return after treatment, whether conservative, office-based, or surgical. Prevention lowers this risk considerably.
Maintain a high-fibre diet permanently, not only during an active episode.
Keep up good fluid intake every day.
Avoid long periods of straining. Avoid long periods sitting on the toilet, as a lasting habit.
Stay physically active, since a sedentary lifestyle raises the risk of constipation and straining.
Treat constipation early, rather than waiting for symptoms to become severe.
Share this advice with every patient, not only those who have just finished treatment. Prevention is far easier, and far less costly, than repeated treatment.
10.14 Special Considerations in Older Patients
Older patients often have other medical conditions that affect treatment choice. Many take blood-thinning medication, for heart or vascular disease. This raises the risk of bleeding with any procedure, including simple office treatment. Discuss with the patient's physician before stopping or adjusting these medicines. Never stop a blood thinner without proper advice. This can carry its own serious risk.
Older patients may also have reduced sphincter tone, from age or from past childbirth injury. This raises the risk of some degree of leakage after surgery. Assess this carefully before major surgery. Discuss the risk clearly with the patient.
10.15 Common Mistakes to Avoid
Diagnosing piles from history alone, without a full examination.
Missing a red flag symptom, because piles were found and no further assessment was done.
Offering surgery for first or second degree piles, before a fair trial of conservative treatment.
Delaying surgery in fourth degree piles, or in strangulated piles, out of excessive caution.
Failing to explain the grade of piles, and the reasoning behind the chosen treatment, to the patient.
Treating a thrombosed external pile the same way in every patient, without considering how many hours or days have passed since onset.
10.16 Recording and Follow-Up
Record the grade of piles, their position on the clock face, and the treatment plan chosen. For example: "Second degree piles at 3, 7, and 11 o'clock. Plan: rubber band ligation, given failure of dietary measures over four weeks." Arrange a clear follow-up visit. Check the response to treatment. Plan further steps if needed.
10.17 Why This Chapter Matters
Piles are common, but they must never be treated carelessly. A clear grading system guides the right treatment for each patient. A full examination protects against missing a more serious diagnosis. A staged approach moves from conservative treatment, to office procedures, to surgery. This gives each patient the least invasive treatment that will work. The next chapter turns to fissure-in-ano, another very common, and often misunderstood, anorectal condition.